
What causes cystic fibrosis?
 Reviewed by
Cystic fibrosis (CF) is a genetic condition caused by disease-causing changes, or mutations, in both copies of the cystic fibrosis transmembrane conductance regulator (CFTR) gene. A person inherits one copy from each biological parent.
The CFTR gene provides instructions for making CFTR protein. Mutations are changes in the gene’s DNA sequence that can affect how much protein is made, whether it reaches the cell surface, or how well it works there.
CFTR normally helps chloride and bicarbonate — tiny charged particles — move across cell membranes. When it does not work properly, this disrupts salt transport and the water movement that depends on it. Mucus becomes dehydrated, thick, and sticky, contributing to breathing and digestive problems.
CFTR dysfunction also prevents sweat glands from reabsorbing salt properly, causing unusually salty sweat. Measuring salt content in sweat is therefore a key part of CF diagnosis.
Understanding what causes CF can help explain its symptoms, how it runs in families, and why some treatments work for certain mutations. Knowing the basics can also help people prepare for conversations about genetic testing, treatment, and family planning.
CF causes
CF is caused by disease-causing mutations in the CFTR gene. These changes affect the instructions cells use to make CFTR protein.
Some mutations prevent cells from making functional protein. Others affect how the protein is processed or transported to the cell surface, how its channel opens, or how efficiently particles move through it. These changes can disrupt CFTR function even when protein is present.
Without normal chloride and bicarbonate transport, water movement across cell membranes is also affected. This leaves mucus thicker and stickier than usual. The mucus can clog airways and ducts that carry digestive juices from the pancreas, causing problems in the lungs and digestive system.
How is CF inherited?
CF follows an autosomal recessive inheritance pattern. This means a person generally develops CF when they inherit a disease-causing CFTR variant in each copy of the gene, one from each biological parent. The two variants do not have to be the same.
Everyone has two copies of the CFTR gene. For each pregnancy, each parent passes on one of their two copies. Which copy is passed on is independent of what happened in previous pregnancies.
What does it mean to be a CF carrier?
A person with a disease-causing variant in just one copy of the CFTR gene is a CF carrier. Carriers do not have CF, but they can pass the variant to their biological children.
CF can affect people of any background. However, CF-causing genetics are more common in some populations. Estimates of carrier frequency include:
- 1 in 22 to 27 people of Northern European heritage
- 1 in 29 people of Ashkenazi Jewish heritage
- 1 in 36 people of Bahraini heritage
- 1 in 46 people of Mexican heritage
- 1 in 85 people of African heritage
These population estimates do not determine an individual’s carrier status. Family history and genetic testing can help clarify a person’s chances of carrying a variant.
Some disease-causing variants are more common in certain populations. Identifying the specific variants matters because they can affect CFTR function and eligibility for treatments that target particular protein defects.
Standard carrier screening panels look for a selection of known disease-causing CFTR variants and may miss rare mutations. A negative result lowers the chance of being a carrier but does not eliminate it. This remaining chance is called residual risk. A genetic counselor can explain what a result means based on the test used and the person’s family history and background.
What are the chances of passing on CF?
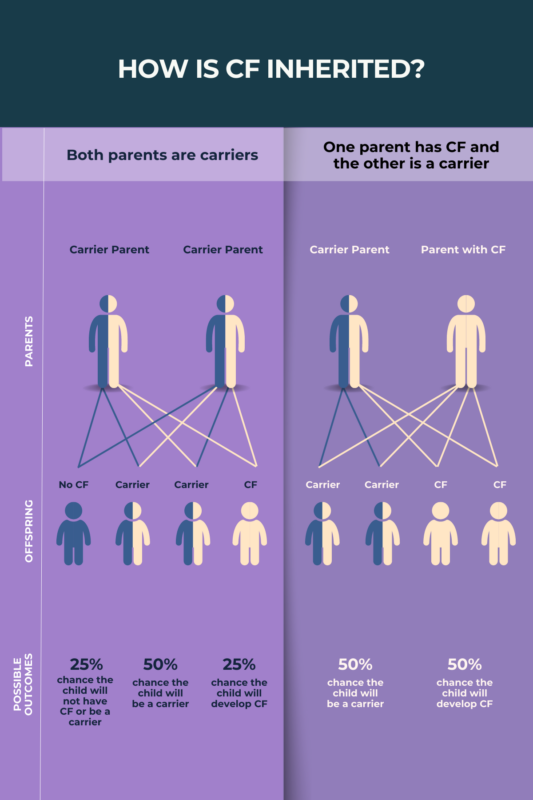
The chance of passing on CF depends on whether each biological parent has CF, is a carrier, or carries no disease-causing CFTR variants.
When both parents are carriers, each pregnancy has a:
- 25% chance that the child will have CF
- 50% chance that the child will be a carrier but will not have CF
- 25% chance that the child will neither have CF nor be a carrier
When one parent has CF and the other is a carrier, each pregnancy has a:
- 50% chance that the child will have CF
- 50% chance that the child will be a carrier but will not have CF
A parent with CF passes a disease-causing variant to every biological child. If the other parent has no disease-causing CFTR variants, every child will be a carrier but will not have CF. If both parents have CF, every child will inherit a disease-causing variant from each parent and have CF.
These probabilities apply independently to every pregnancy. Having one child with CF does not change the chances for another child.
How CFTR mutations affect the body
More than 2,500 mutations in the CFTR gene have been reported, although not all cause CF. Disease-causing types of CFTR mutations can affect the protein in several ways, including:
- preventing production of functional protein
- disrupting protein processing and delivery to the cell surface
- preventing the channel’s gate from opening properly
- reducing how efficiently particles pass through an open channel
- reducing the amount of functional protein produced
- causing protein to be removed from the cell surface too quickly
Normally, CFTR sits at the surface of certain cells and acts like a gated channel. When the gate opens, chloride and bicarbonate can pass through. CFTR does not carry water directly; water movement changes in response to the movement of these particles.
When CFTR does not work properly, the resulting changes in salt and water transport leave mucus dehydrated and sticky. This mucus can block airways and pancreatic ducts. CFTR dysfunction can also affect other parts of the body, including the reproductive system.
Less remaining CFTR function is often associated with certain complications, particularly pancreatic insufficiency. However, the specific combination of variants, other genes, infections, environmental factors, access to care, and treatment also influence symptoms. Mutation class alone cannot predict an individual’s disease course.
How does CFTR mutation type affect disease severity?
CF symptoms and complications vary from person to person. The mutations a person has can help explain how their CFTR protein works, but they do not provide a complete picture of how CF will affect them.
Different classification systems group mutations by their effects on the protein. The Cystic Fibrosis Foundation describes five main groups, while a commonly used six-class system separates problems with protein stability at the cell surface into a sixth group.
The six classes are:
- Class 1 — Protein production: Cells make little or no functional CFTR protein.
- Class 2 — Protein processing: The protein does not fold correctly and is usually broken down before it reaches the cell surface.
- Class 3 — Gating: The protein reaches the cell surface, but its channel does not open properly.
- Class 4 — Conduction: The protein reaches the cell surface and its channel can open, but particles pass through less efficiently.
- Class 5 — Reduced protein production: Cells make some functional CFTR protein, but in smaller amounts than usual.
- Class 6 — Reduced protein stability: The protein reaches the cell surface but is removed or broken down too quickly.
These categories describe the main protein defects; some mutations can have more than one effect.
Classes 1, 2, and 3 often involve very little CFTR function. Certain combinations of these variants increase the likelihood of pancreatic insufficiency, meaning the pancreas does not deliver enough digestive enzymes to the intestine to break down food properly. However, mutation class cannot reliably predict how quickly lung disease will progress.
Classes 4 and 5 generally leave some CFTR function and are often associated with a lower likelihood of pancreatic insufficiency. People with these variants can still develop significant lung disease and other complications.
Some variants can be treated with CFTR modulators, medicines that help improve CFTR protein function. Variants that produce no CFTR protein generally lack a target for these medicines. Treatment eligibility depends on the specific variant and the medicine’s approved use, rather than mutation class alone.
Many factors beyond the CFTR gene affect the severity of CF. A CF care team can explain what genetic results may mean alongside symptoms, test results, and treatment response.
Questions for a healthcare team or genetic counselor
People with CF, carriers, and their families may find it helpful to ask:
- What specific CFTR mutations do I have?
- How do these mutations affect the amount or function of CFTR protein?
- Which mutation classes do my variants fall into?
- What can my genetic results tell me about CF, and what can’t they predict?
- What other factors could affect how CF progresses?
- Are my variants associated with pancreatic, lung, digestive, or reproductive problems?
- Am I eligible for CFTR modulators or another treatment that targets my variants?
- Should my partner have CF carrier testing?
- What are the chances of my child having CF or being a carrier?
- What reproductive options are available to us?
- Could I still be a carrier after a negative screening test?
- Should other family members consider carrier or genetic testing?
- How do my family history and background affect the interpretation of my results?
- How can a genetic counselor help with treatment or family planning decisions?
Cystic Fibrosis News Today is strictly a news and information website about the disease. It does not provide medical advice, diagnosis, or treatment. This content is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Never disregard professional medical advice or delay in seeking it because of something you have read on this website.



